Chapter 15. The Digestive System
15.2 The Mouth, Pharynx, and Esophagus
Learning Objectives
By the end of this section, you will be able to:
- Describe the structures of the mouth, including its three accessory digestive organs
- Describe adult dentition according to tooth name, location, and function
- Describe the process of swallowing, including the roles of the tongue, upper esophageal sphincter, and epiglottis
- Trace the pathway food follows from ingestion into the mouth through release into the stomach
In this section, you will examine the anatomy and functions of the three main organs of the upper alimentary canal—the mouth, pharynx, and esophagus—as well as three associated accessory organs—the tongue, salivary glands, and teeth.
The Mouth
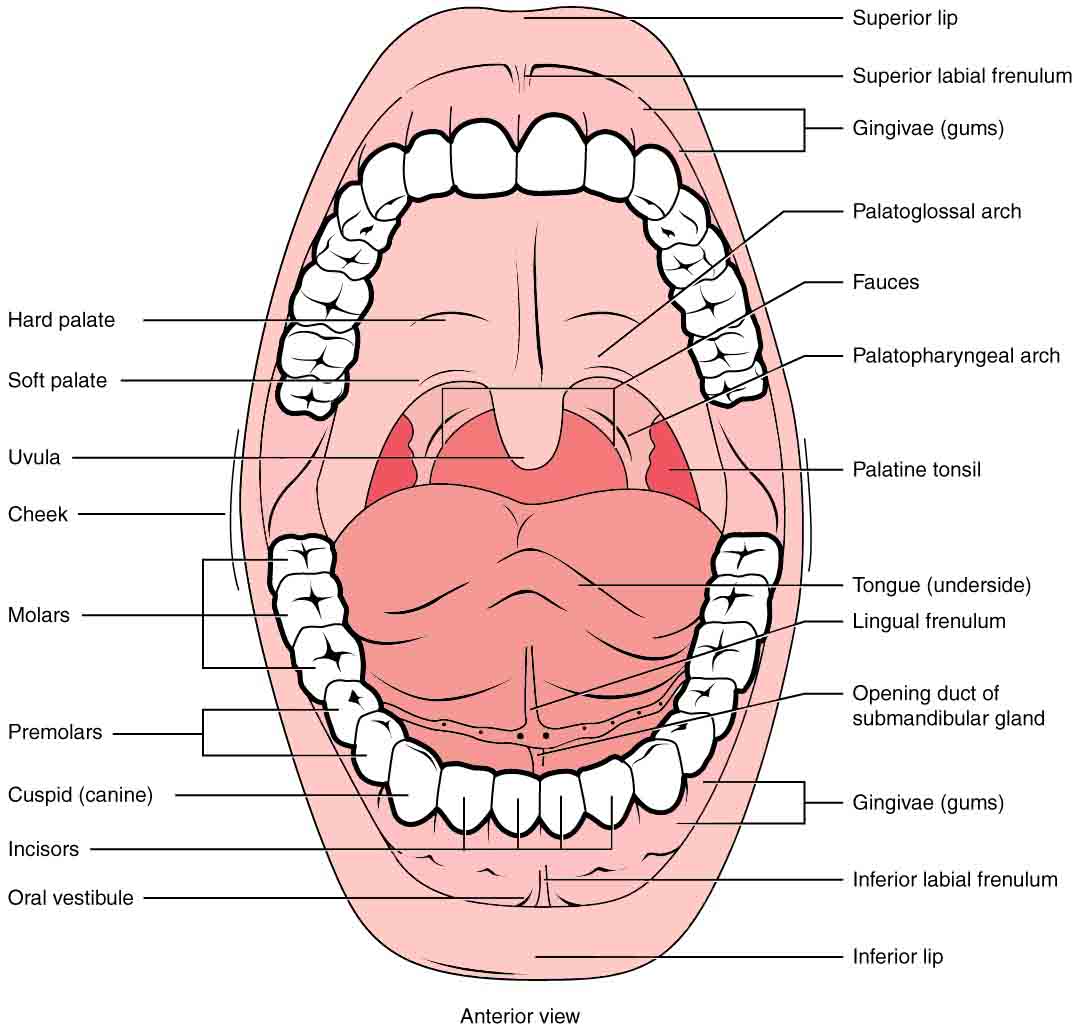
The cheeks, tongue, and palate frame the mouth, which is also called the oral cavity (or buccal cavity). The structures of the mouth are illustrated in Figure 15.2.1.
At the entrance to the mouth are the lips, or labia (singular labium). Their outer covering is skin, which transitions to a mucous membrane in the mouth proper. Lips are very vascular with only a thin layer of keratinized epithelium and therefore they look red due to the red blood cell color showing through the thin, transparent epithelium.
The pocket-like part of the mouth that is framed on the inside by the gums and teeth, and on the outside by the cheeks and lips is called the oral vestibule. Moving farther into the mouth, the opening between the oral cavity and throat (oropharynx) is called the fauces (like the kitchen “faucet”). The main open area of the mouth, or oral cavity proper, runs from the gums and teeth to the fauces.
When you are chewing, you do not find it difficult to breathe simultaneously. The next time you have food in your mouth, notice how the arched shape of the roof of your mouth allows you to handle both digestion and respiration at the same time. This arch is called the palate. The anterior region of the palate serves as a wall (or septum) between the oral and nasal cavities as well as a rigid shelf against which the tongue can push food. It is created by the maxillary and palatine bones of the skull and, given its bony structure, is known as the hard palate. If you run your tongue along the roof of your mouth, you’ll notice that the hard palate ends in the posterior oral cavity, and the tissue becomes fleshier. This part of the palate, known as the soft palate, is composed mainly of skeletal muscle. You can therefore manipulate, subconsciously, the soft palate—for instance, to yawn, swallow, or sing (Figure 15.2.1).
Accessory Structures of the Mouth
The mouth contains several important accessory structures involved in the initial steps of both mechanical breakdown of food. These structures include the tongue, salivary glands, and teeth.
The Tongue
Perhaps you have heard it said that the tongue is the strongest muscle in the body. Those who stake this claim cite its strength proportionate to its size. Although it is difficult to quantify the relative strength of different muscles, it remains indisputable that the tongue is a workhorse, facilitating ingestion, mechanical digestion, chemical digestion (lingual lipase), sensation (of taste, texture, and temperature of food), swallowing, and vocalization.
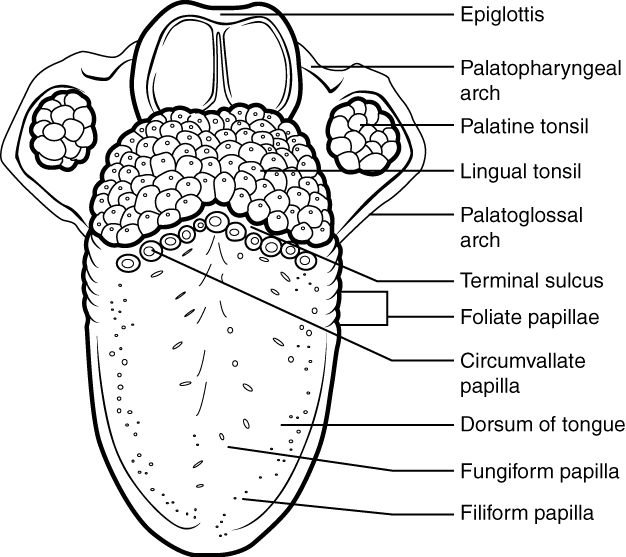
The top and sides of the tongue are studded with papillae, extensions of lamina propria of the mucosa, which are covered in stratified squamous epithelium (Figure 15.2.2). Lingual glands in the lamina propria of the tongue secrete mucus and a watery serous fluid that contains the enzyme lingual lipase, which plays a minor role in breaking down triglycerides but does not begin working until it is activated in the stomach.
The Salivary Glands
Many small salivary glands are housed within the mucous membranes of the mouth and tongue. These minor exocrine glands are constantly secreting saliva, either directly into the oral cavity or indirectly through ducts, even while you sleep. In fact, an average of 1 to 1.5 liters of saliva is secreted each day. Usually just enough saliva is present to moisten the mouth and teeth. Secretion increases when you eat, because saliva is essential to moisten food and initiate the chemical breakdown of carbohydrates. Small amounts of saliva are also secreted by the labial glands in the lips. In addition, the buccal glands in the cheeks, palatal glands in the palate, and lingual glands in the tongue help ensure that all areas of the mouth are supplied with adequate saliva.
The Major Salivary Glands
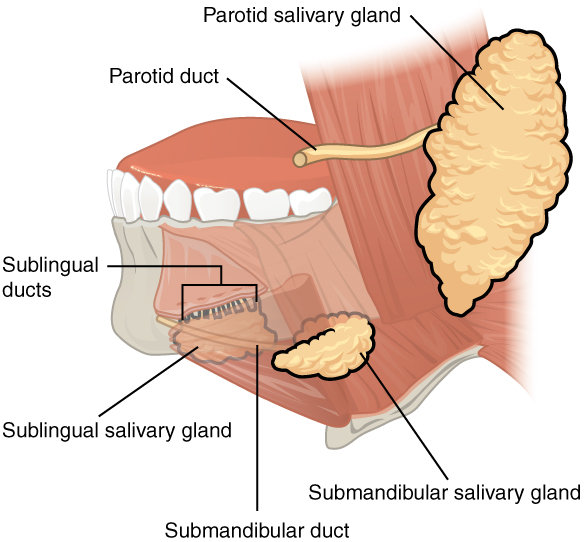
Outside the oral mucosa are three pairs of major salivary glands, which secrete the majority of saliva into ducts that open into the mouth:
- The submandibular glands, which are in the floor of the mouth, secrete saliva into the mouth through the submandibular ducts.
- The sublingual glands, which lie below the tongue, use the lesser sublingual ducts to secrete saliva into the oral cavity.
- The parotid glands lie between the skin and the masseter muscle, near the ears. They secrete saliva into the mouth through the parotid duct, which is located near the second upper molar tooth (Figure 15.2.3).
Saliva
Saliva is essentially (95.5%) water. The remaining 4.5% is a complex mixture of ions, glycoproteins, enzymes, growth factors, and waste products. Perhaps the most important ingredient in salvia from the perspective of digestion is the enzyme salivary amylase, which initiates the breakdown of carbohydrates. Food does not spend enough time in the mouth to allow all the carbohydrates to break down, but salivary amylase continues acting until it is inactivated by stomach acids. Bicarbonate and phosphate ions function as chemical buffers, maintaining saliva at a pH between 6.35 and 6.85. Salivary mucus helps lubricate food, facilitating movement in the mouth, bolus formation, and swallowing. Saliva contains immunoglobulin A, which prevents microbes from penetrating the epithelium, and lysozyme, which makes saliva antimicrobial. Saliva also contains epidermal growth factor, which might have given rise to the adage “a mother’s kiss can heal a wound.”
Each of the major salivary glands secretes a unique formulation of saliva according to its cellular makeup. For example, the parotid glands secrete a watery solution that contains salivary amylase. The submandibular glands have cells similar to those of the parotid glands, as well as mucus-secreting cells. Therefore, saliva secreted by the submandibular glands also contains amylase but in a liquid thickened with mucus. The sublingual glands contain mostly mucous cells, and they secrete the thickest saliva with the least amount of salivary amylase.
Homeostatic Imbalances – The Parotid Glands: Mumps
Infections of the nasal passages and pharynx can attack any salivary gland. The parotid glands are the usual site of infection with the virus that causes mumps (paramyxovirus). Mumps manifests by enlargement and inflammation of the parotid glands, causing a characteristic swelling between the ears and the jaw. Symptoms include fever and throat pain, which can be severe when swallowing acidic substances such as orange juice.
In about one-third of men who are past puberty, mumps also causes testicular inflammation, typically affecting only one testis and rarely resulting in sterility. With the increasing use and effectiveness of mumps vaccines, the incidence of mumps has decreased dramatically. According to the U.S. Centers for Disease Control and Prevention (CDC), the number of mumps cases dropped from more than 150,000 in 1968 to fewer than 1700 in 1993 to only 357 reported cases in 2024 (CDC, 2025). Mumps outbreaks do still occur in the United States and vaccination can reduce the severity of symptoms and complications for those who catch the disease. During an outbreak, individuals at increased risk of exposure may be advised to get an additional dose of the MMR vaccine; these individuals are those likely to have close contact with a person who has mumps, either due to shared living space, shared sports equipment or drinks, or intimate relationships.
Regulation of Salivation
The autonomic nervous system regulates salivation (the secretion of saliva). In the absence of food, parasympathetic stimulation keeps saliva flowing at just the right level for comfort as you speak, swallow, sleep, and generally go about life. Over-salivation can occur, for example, if you are stimulated by the smell of food, but that food is not available for you to eat. Drooling is an extreme instance of the overproduction of saliva. During times of stress, such as before speaking in public, sympathetic stimulation takes over, reducing salivation and producing the symptom of dry mouth often associated with anxiety. When you are dehydrated, salivation is reduced, causing the mouth to feel dry and prompting you to take action to quench your thirst.
Salivation can be stimulated by the sight, smell, and taste of food. It can even be stimulated by thinking about food. You might notice whether reading about food and salivation right now has had any effect on your production of saliva.
How does the salivation process work while you are eating? Food contains chemicals that stimulate taste receptors on the tongue, which send impulses to the superior and inferior salivatory nuclei in the brain stem. These two nuclei then send back parasympathetic impulses through fibers in the glossopharyngeal and facial nerves, which stimulate salivation. Even after you swallow food, salivation is increased to cleanse the mouth and to water down and neutralize any irritating chemical remnants, such as that hot sauce in your burrito. Most saliva is swallowed along with food and is reabsorbed, so that fluid is not lost.
The Teeth
The teeth, or dentes (singular dens), are organs similar to bones that you use to tear, grind, and otherwise mechanically break down food.
Types of Teeth
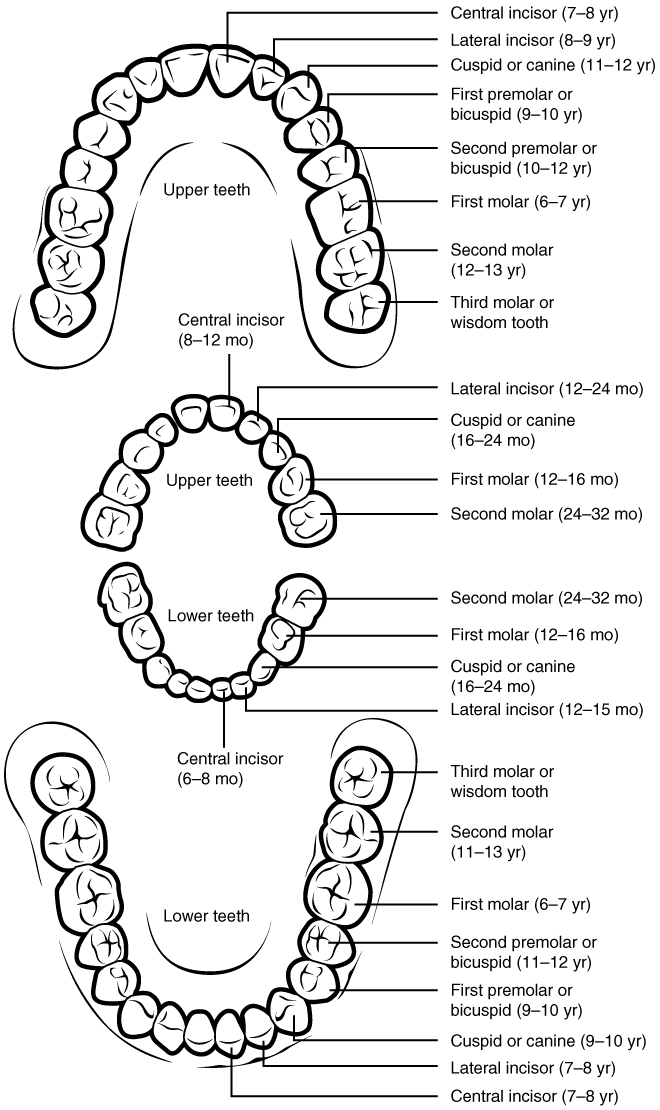
During the course of your lifetime, you have two sets of teeth (one set of teeth is a dentition). Your 20 deciduous teeth, or baby teeth, first begin to appear at about 6 months of age. Between approximately age 6 and 12, these teeth are replaced by 32 permanent teeth. Moving from the center of the mouth toward the side, these are as follows (Figure 15.2.4):
- The eight incisors, four top and four bottom, are the sharp front teeth you use for biting into food.
- The four cuspids (or canines) flank the incisors and have a pointed edge (cusp) to tear up food. These fang-like teeth are superb for piercing tough or fleshy foods.
- Posterior to the cuspids are the eight premolars (or bicuspids), which have an overall flatter shape with two rounded cusps useful for mashing foods.
- The most posterior and largest are the 12 molars, which have several pointed cusps used to crush food so it is ready for swallowing. The third members of each set of three molars, top and bottom, are commonly referred to as the wisdom teeth, because their eruption is commonly delayed until early adulthood. It is not uncommon for wisdom teeth to fail to erupt; that is, they remain impacted. In these cases, the teeth are typically removed by orthodontic surgery.
| Structure | Action | Outcome |
|---|---|---|
| Lips and cheeks | Confine food between teeth |
|
| Salivary glands | Secrete saliva |
|
| Tongue’s muscles | Move tongue sideways, and in and out
Change tongue shape |
|
| Taste buds | Sense food in mouth and sense taste |
|
| Lingual glands | Secrete lingual lipase |
|
| Teeth | Shred and crush food |
|
The Pharynx
The pharynx (throat) is involved in both digestion and respiration. It receives food and air from the mouth, and air from the nasal cavities. When food enters the pharynx, involuntary muscle contractions close off the air passageways.
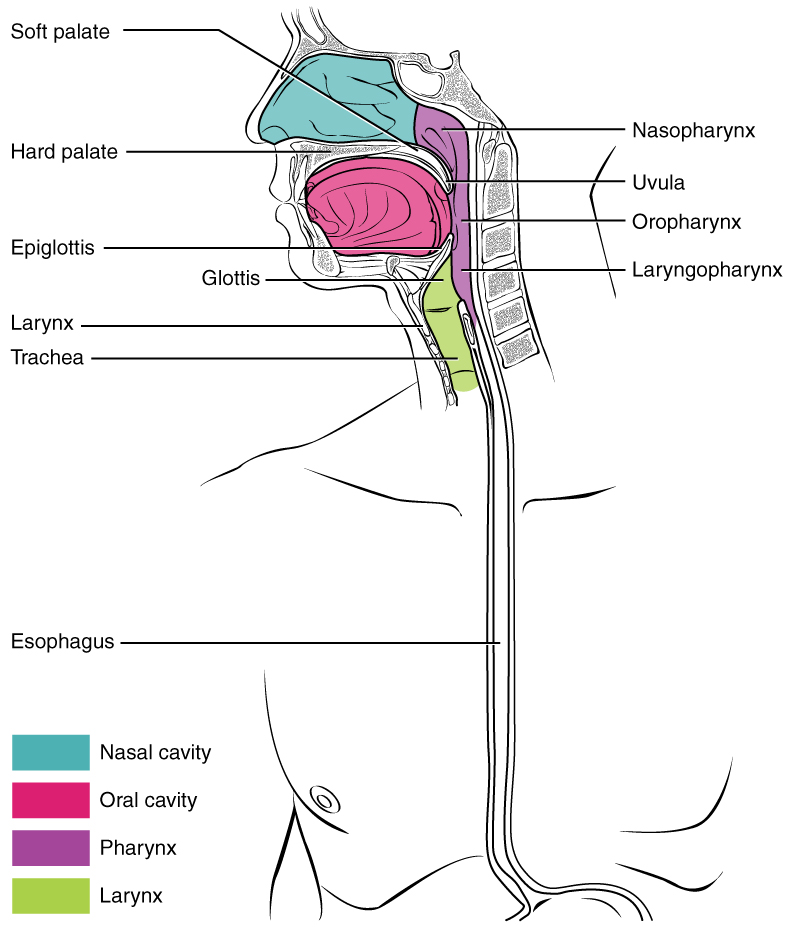
A short tube of skeletal muscle lined with a mucous membrane, the pharynx runs from the posterior oral and nasal cavities to the opening of the esophagus and larynx. It has three subdivisions. The most superior, the nasopharynx, is involved only in breathing and speech. The other two subdivisions, the oropharynx and the laryngopharynx, are used for both breathing and digestion. The oropharynx begins inferior to the nasopharynx and is continuous below with the laryngopharynx (Figure 15.2.5). The inferior border of the laryngopharynx connects to the esophagus, whereas the anterior portion connects to the larynx, allowing air to flow into the bronchial tree.
Histologically, the wall of the oropharynx is similar to that of the oral cavity. The mucosa includes a stratified squamous epithelium that is endowed with mucus-producing glands. During swallowing, the elevator skeletal muscles of the pharynx contract, raising and expanding the pharynx to receive the bolus of food. Once received, these muscles relax and the constrictor muscles of the pharynx contract, forcing the bolus into the esophagus and initiating peristalsis.
Usually during swallowing, the soft palate and uvula rise reflexively to close off the entrance to the nasopharynx. At the same time, the larynx is pulled superiorly and the cartilaginous epiglottis, its most superior structure, folds inferiorly, covering the glottis (the opening to the larynx); this process effectively blocks access to the trachea and bronchi. When the food “goes down the wrong way,” it goes into the trachea. When food enters the trachea, the reaction is to cough, which usually forces the food up and out of the trachea, and back into the pharynx.
The Esophagus
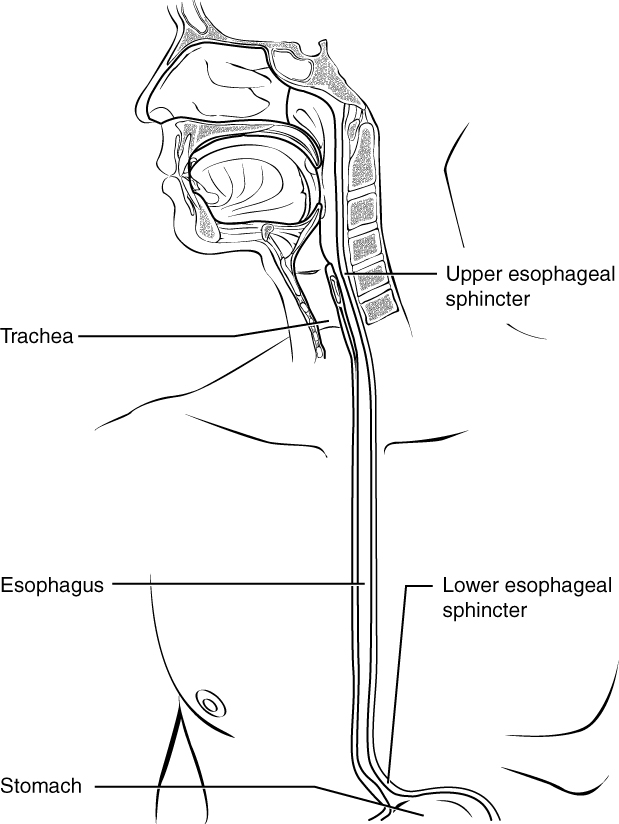
The esophagus is a muscular tube that connects the pharynx to the stomach. It is approximately 25.4 centimeters (10 inches) in length, located posterior to the trachea, and remains in a collapsed form when not engaged in swallowing. As you can see in Figure 15.2.6, the esophagus runs a mainly straight route through the mediastinum of the thorax. To enter the abdomen, the esophagus penetrates the diaphragm through an opening called the esophageal hiatus.
Passage of Food through the Esophagus
The upper esophageal sphincter controls the movement of food from the pharynx into the esophagus. The upper two-thirds of the esophagus consists of both smooth and skeletal muscle fibers, with the latter fading out in the bottom third of the esophagus. Rhythmic waves of peristalsis, which begin in the upper esophagus, propel the bolus of food toward the stomach. Meanwhile, secretions from the esophageal mucosa lubricate the esophagus and food. Food passes from the esophagus into the stomach at the lower esophageal sphincter (also called the gastroesophageal or cardiac sphincter). Recall that sphincters are muscles that surround tubes and serve as valves, closing the tube when the sphincters contract and opening it when they relax. The lower esophageal sphincter relaxes to let food pass into the stomach, and then contracts to prevent stomach acids from backing up into the esophagus. Surrounding this sphincter is the muscular diaphragm, which helps close off the sphincter when no food is being swallowed. When the lower esophageal sphincter does not completely close, the stomach’s contents can reflux (that is, back up into the esophagus), causing heartburn or gastroesophageal reflux disease (GERD).
Histology of the Esophagus
The mucosa of the esophagus is made up of an epithelial lining that contains non-keratinized, stratified squamous epithelium. This epithelium protects against erosion from food particles. The mucosa’s lamina propria contains mucus-secreting glands. The muscularis layer changes according to location: In the upper third of the esophagus, the muscularis is skeletal muscle. In the middle third, it is both skeletal and smooth muscle. In the lower third, it is smooth muscle. As mentioned previously, the most superficial layer of the esophagus is called the adventitia, not the serosa. In contrast to the stomach and intestines, the loose connective tissue of the adventitia is not covered by a fold of visceral peritoneum. The digestive functions of the esophagus are identified in Table 15.2.2.
| Action | Outcome |
|---|---|
| Upper esophageal sphincter relaxation | Allows the bolus to move from the laryngopharynx to the esophagus |
| Peristalsis | Propels the bolus through the esophagus |
| Lower esophageal sphincter relaxation | Allows the bolus to move from the esophagus into the stomach and prevents chime from entering the esophagus |
| Mucus secretion | Lubricates the esophagus, allowing easy passage of the bolus |
Deglutition
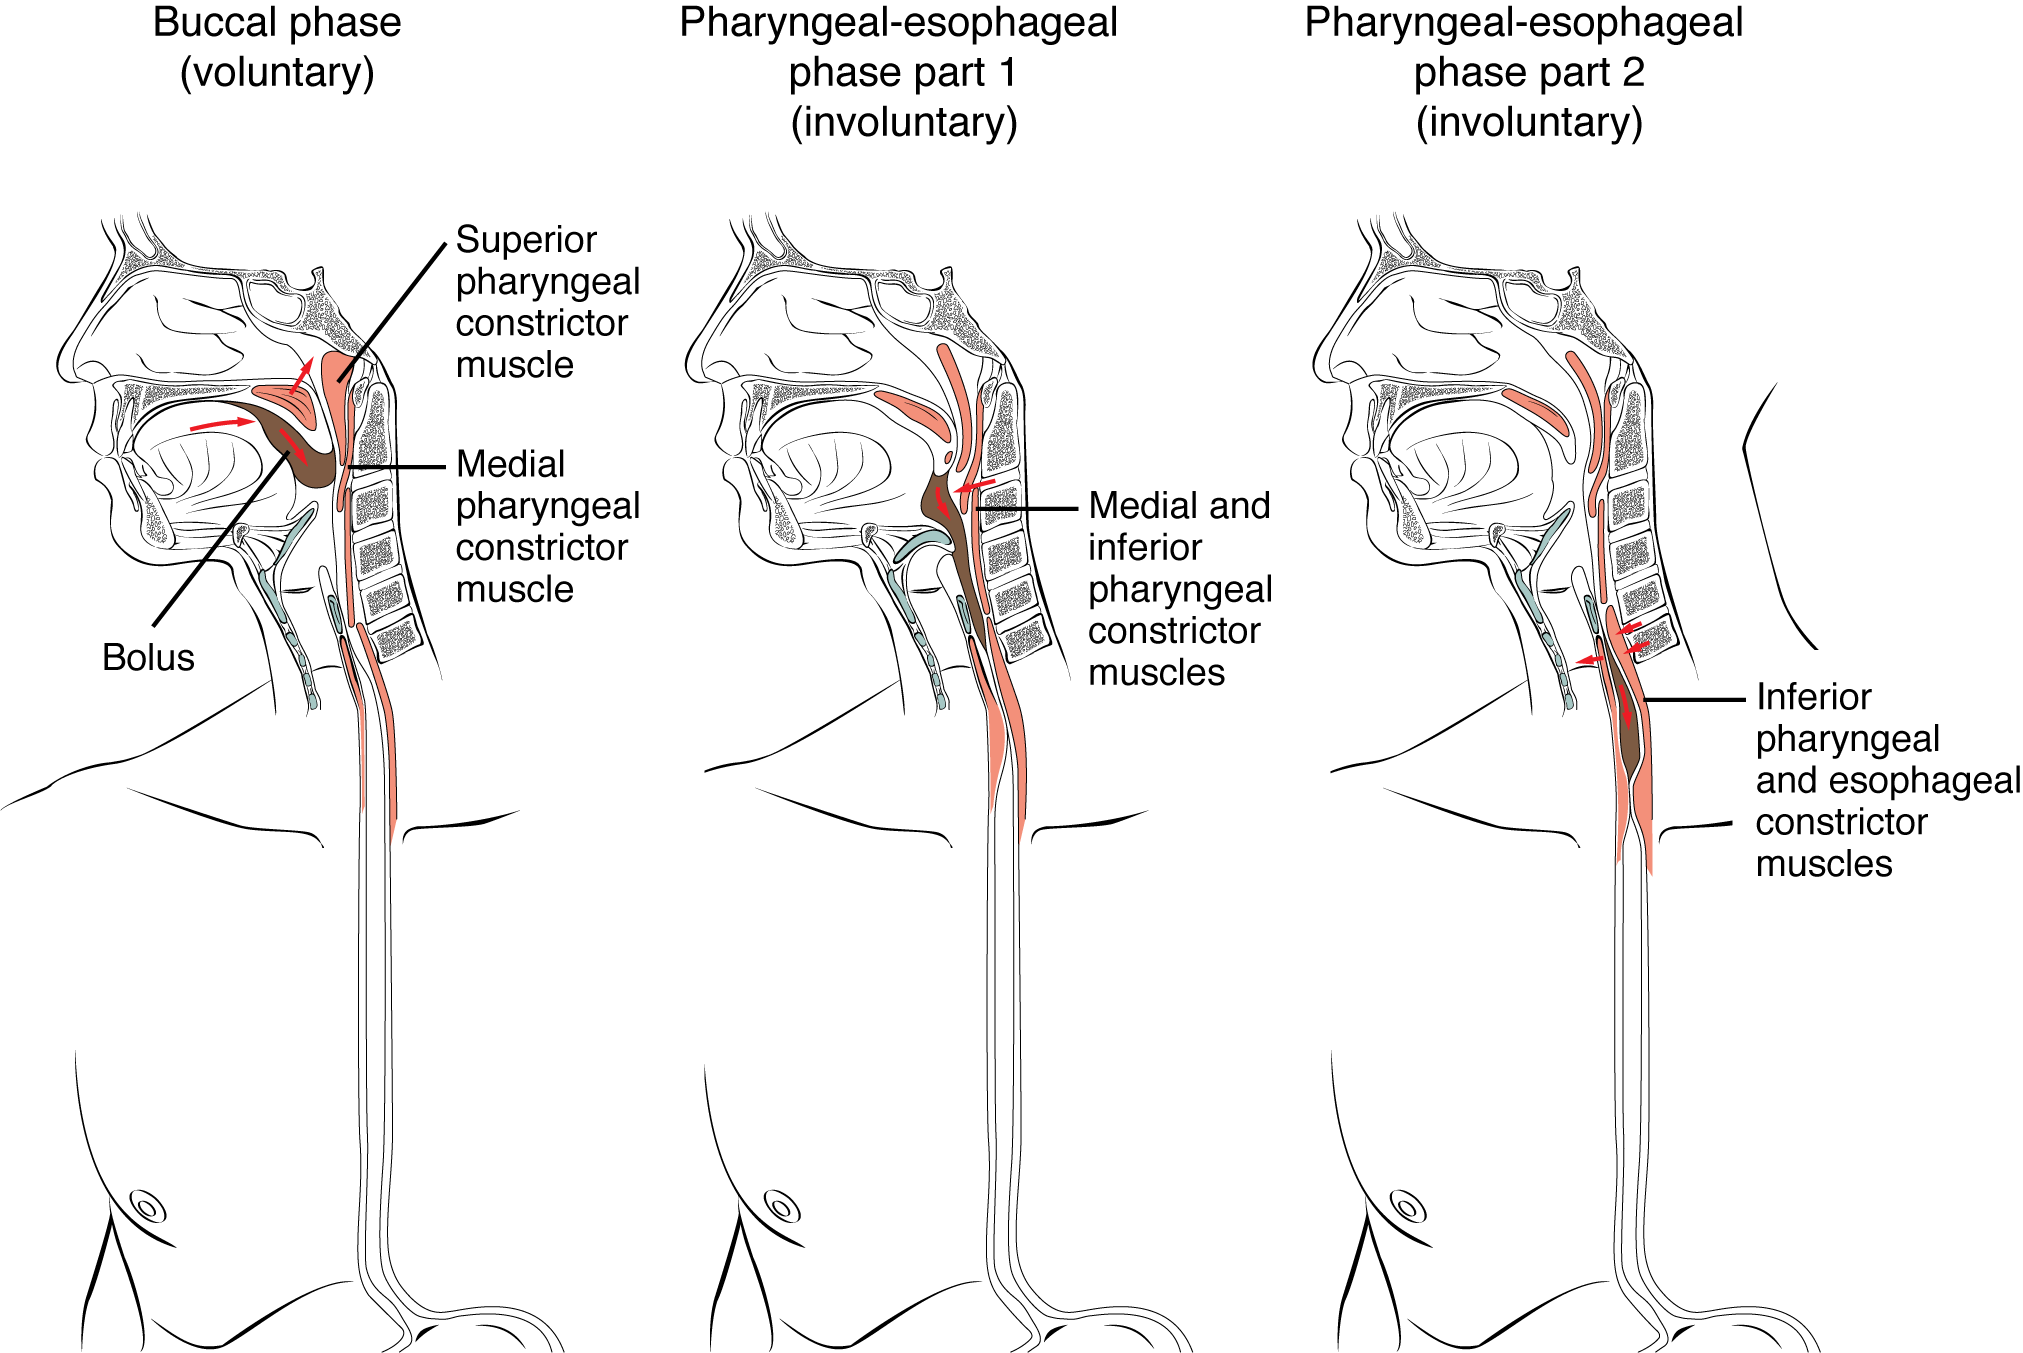
Deglutition is another word for swallowing—the movement of food from the mouth to the stomach. The entire process takes about 4 to 8 seconds for solid or semisolid food, and about 1 second for very soft food and liquids. Although this sounds quick and effortless, deglutition is, in fact, a complex process that involves both the skeletal muscle of the tongue and the muscles of the pharynx and esophagus. It is aided by the presence of mucus and saliva. There are three stages in deglutition: the voluntary phase, the pharyngeal phase, and the esophageal phase (Figure 15.2.7). The autonomic nervous system controls the latter two phases.
The Voluntary Phase
The voluntary phase of deglutition (also known as the oral or buccal phase) is so called because you can control when you swallow food. In this phase, chewing has been completed and swallowing is set in motion. The tongue moves upward and backward against the palate, pushing the bolus to the back of the oral cavity and into the oropharynx. Other muscles keep the mouth closed and prevent food from falling out. At this point, the two involuntary phases of swallowing begin.
The Pharyngeal Phase
In the pharyngeal phase, stimulation of receptors in the oropharynx sends impulses to the deglutition center (a collection of neurons that controls swallowing) in the medulla oblongata. Impulses are then sent back to the uvula and soft palate, causing them to move upward and close off the nasopharynx. The laryngeal muscles also constrict to prevent aspiration of food into the trachea. At this point, deglutition apnea takes place, which means that breathing ceases for a very brief time. Contractions of the pharyngeal constrictor muscles move the bolus through the oropharynx and laryngopharynx. Relaxation of the upper esophageal sphincter then allows food to enter the esophagus.
The Esophageal Phase
The entry of food into the esophagus marks the beginning of the esophageal phase of deglutition and the initiation of peristalsis. As in the previous phase, the complex neuromuscular actions are controlled by the medulla oblongata. Peristalsis propels the bolus through the esophagus and toward the stomach. The circular muscle layer of the muscularis contracts, pinching the esophageal wall and forcing the bolus forward. At the same time, the longitudinal muscle layer of the muscularis also contracts, shortening this area and pushing out its walls to receive the bolus. In this way, a series of contractions keeps moving food toward the stomach. When the bolus nears the stomach, distention of the esophagus initiates a short reflex relaxation of the lower esophageal sphincter that allows the bolus to pass into the stomach. During the esophageal phase, esophageal glands secrete mucus that lubricates the bolus and minimizes friction.
External Website

Watch this animation to see how swallowing is a complex process that involves the nervous system to coordinate the actions of upper respiratory and digestive activities. During which stage of swallowing is there a risk of food entering respiratory pathways, and how is this risk blocked?
Section Review
In the mouth, the tongue and the teeth begin mechanical digestion, and saliva begins chemical digestion. The pharynx, which plays roles in breathing and vocalization as well as digestion, runs from the nasal and oral cavities superiorly to the esophagus inferiorly (for digestion) and to the larynx anteriorly (for respiration). During deglutition (swallowing), the soft palate rises to close off the nasopharynx, the larynx elevates, and the epiglottis folds over the glottis. The esophagus includes an upper esophageal sphincter made of skeletal muscle, which regulates the movement of food from the pharynx to the esophagus. It also has a lower esophageal sphincter, made of smooth muscle, which controls the passage of food from the esophagus to the stomach. Cells in the esophageal wall secrete mucus that eases the passage of the food bolus.
Interactive Link Questions
Watch this animation [New Tab] to see how swallowing is a complex process that involves the nervous system to coordinate the actions of upper respiratory and digestive activities.
Review Questions
Critical Thinking Questions
Glossary
- bolus
- mass of chewed food
- cuspid
- pointed tooth used for tearing and shredding food (also canine)
- deciduous tooth
- one of 20 “baby teeth”
- deglutition
- three-stage process of swallowing
- dens
- tooth
- dentition
- set of teeth
- esophagus
- muscular tube that runs from the pharynx to the stomach
- fauces
- opening between the oral cavity and the oropharynx
- incisor
- midline, chisel-shaped tooth used for cutting into food
- labium
- lip
- laryngopharynx
- part of the pharynx that functions in respiration and digestion
- lingual lipase
- digestive enzyme from glands in the tongue that acts on triglycerides
- lower esophageal sphincter
- smooth muscle sphincter that regulates food movement from the esophagus to the stomach
- molar
- tooth used for crushing and grinding food
- oral cavity
- mouth (also buccal cavity)
- oropharynx
- part of the pharynx continuous with the oral cavity that functions in respiration and digestion
- parotid gland
- one of a pair of major salivary glands located inferior and anterior to the ears
- permanent tooth
- one of 32 adult teeth
- pharynx
- throat
- premolar
- transitional tooth used for mastication, crushing, and grinding food (also bicuspid)
- saliva
- aqueous solution of proteins and ions secreted into the mouth by the salivary glands
- salivary amylase
- digestive enzyme in saliva that acts on starch
- salivary gland
- an exocrine gland that secretes a digestive fluid called saliva
- salivation
- secretion of saliva
- soft palate
- posterior region of the bottom portion of the nasal cavity that consists of skeletal muscle
- sublingual gland
- one of a pair of major salivary glands located beneath the tongue
- submandibular gland
- one of a pair of major salivary glands located in the floor of the mouth
- tongue
- accessory digestive organ of the mouth, the bulk of which is composed of skeletal muscle
- upper esophageal sphincter
- skeletal muscle sphincter that regulates food movement from the pharynx to the esophagus
Glossary Flashcards
Reference
Centers for Disease Control and Prevention. (2025, September 12). Mumps cases and outbreaks. U.S. Department of Health & Human Services. https://www.cdc.gov/mumps/outbreaks/index.html
This work, Human Physiology, is adapted from Anatomy & Physiology by OpenStax, licensed under CC BY. This edition, with revised content and artwork, is licensed under CC BY-SA except where otherwise noted.
Images from Anatomy & Physiology by OpenStax are licensed under CC BY except where otherwise noted.
Access the original for free at OpenStax.
Image Descriptions
Figure 15.2.1. This anatomical diagram provides an anterior (front) view of the human oral cavity with the mouth wide open, systematically labeling the key structures visible from this perspective. The outer structures include the superior lip at the top, the inferior lip at the bottom, the superior labial frenulum and inferior labial frenulum (thin tissue connecting the lips to the gums), and the cheeks on the sides. The oral vestibule is the space between the lips/cheeks and the teeth. The teeth are comprehensively labeled, showing incisors at the front, followed by the cuspid (canine) teeth, then premolars, and molars at the back of the mouth. The gingiva (gums) surround the teeth on both upper and lower arches. Within the oral cavity proper, the diagram identifies the hard palate and soft palate forming the roof of the mouth, with the uvula hanging down from the soft palate. The palatoglossal arch and palatopharyngeal arch frame the sides of the opening to the throat, with the palatine tonsils visible between these arches (shown in a darker pink). The tongue is shown from its underside view, with the lingual frenulum visible underneath. Additional features include the fauces (the opening between the oral cavity and throat) and the opening duct of the submandibular gland located under the tongue. [Return to Figure 15.2.1]
Figure 15.2.2. This anatomical illustration presents a superior (top-down) view of the human tongue with the mouth open, detailing the various structures visible on the tongue’s dorsal surface and surrounding oral cavity. At the base of the tongue, near the throat, the epiglottis is labeled at the top of the diagram. The oropharynx region shows the palatopharyngeal arch and palatoglossal arch on either side, with the palatine tonsils positioned between these arches and the lingual tonsils visible at the posterior base of the tongue. The tongue’s surface features several types of papillae, which are small projections that give the tongue its characteristic texture. The terminal sulcus is a V-shaped groove that divides the anterior two-thirds of the tongue from the posterior third. Anterior to this groove are the circumvallate papillae, large dome-shaped structures arranged in a V-pattern. The middle and anterior portions of the tongue display foliate papillae on the sides, fungiform papillae scattered across the surface (appearing as small mushroom-shaped projections), and numerous tiny filiform papillae throughout, which are the most abundant type and give the tongue its rough texture. The dorsum of tongue refers to the upper surface of the tongue itself, which contains all these sensory and textural features essential for taste and tactile sensation. [Return to Figure 15.2.2]
Figure 15.2.3. This anatomical illustration displays the three pairs of major salivary glands and their associated ducts within a side view of the human head and neck. The parotid salivary gland, the largest of the salivary glands, appears as a yellowish, textured mass positioned in front of and below the ear. The parotid duct extends from this gland forward across the cheek, delivering saliva to the oral cavity near the upper teeth. Below the tongue and jaw, the sublingual salivary gland is shown with its associated sublingual ducts, which open beneath the tongue on the floor of the mouth. The submandibular salivary gland is positioned below the lower jaw, with the submandibular duct running from the gland upward to open into the mouth. The illustration uses a cutaway view of the facial tissues and musculature (shown in reddish-pink tones) to reveal the anatomical positioning of these structures relative to visible landmarks such as the teeth and jaw. These three pairs of glands work together to produce saliva, which aids in digestion, maintains oral health, and facilitates speaking and swallowing. [Return to Figure 15.2.3]
Figure 15.2.4. This comprehensive dental chart illustrates the eruption timeline for both primary (baby) teeth and permanent (adult) teeth in humans, displayed through four arch diagrams viewed from above. The top two diagrams show the upper teeth, while the bottom two show the lower teeth, with primary teeth depicted in the smaller central diagrams and permanent teeth in the larger outer diagrams. Each tooth type is clearly labeled with its name and typical eruption age. For primary teeth, the chart indicates that central incisors appear at 6-8 months (lower) or 8-12 months (upper), lateral incisors at 12-15 months (lower) or 12-24 months (upper), cuspids or canines at 16-24 months, first molars at 12-16 months, and second molars at 24-32 months. For permanent teeth, the timeline shows central incisors erupting at 7-8 years, lateral incisors at 8-9 years, cuspids or canines at 9-12 years, first premolars or bicuspids at 9-10 years, second premolars or bicuspids at 10-12 years, first molars at 6-7 years, second molars at 11-13 years, and third molars or wisdom teeth at variable times. The diagrams use a top-down perspective showing the characteristic shapes and surface features of each tooth type, with lines pointing from each tooth to its corresponding label, making it easy to identify both the position and eruption schedule of each tooth in the human dentition. [Return to Figure 15.2.4]
Figure 15.2.5. This anatomical diagram presents a sagittal (side-view) cross-section of the human head, neck, and upper torso, illustrating the upper respiratory and digestive tracts with color-coded regions for clarity. The nasal cavity is shown in teal at the top of the diagram, beginning at the nostrils and extending back to where it connects with the throat. The hard palate and soft palate form the roof of the mouth, separating the nasal cavity from the oral cavity below. The oral cavity, highlighted in pink, contains the tongue as a prominent curved structure. The uvula hangs down from the posterior edge of the soft palate. Behind these cavities lies the pharynx (throat region), shown in purple, which is subdivided into three sections: the nasopharynx (behind the nasal cavity), the oropharynx (behind the oral cavity), and the laryngopharynx (the lowest section). The epiglottis, a flap-like structure, is positioned at the junction between the pharynx and larynx. The larynx (voice box), colored in green, contains the glottis and leads to the trachea (windpipe), which extends downward toward the chest. Parallel to the trachea, the esophagus descends posteriorly, serving as the passageway for food from the pharynx to the stomach. A color-coded legend at the bottom left identifies the nasal cavity, oral cavity, pharynx, and larynx regions, helping readers understand the spatial relationships and functions of these interconnected anatomical structures [Return to Figure 15.2.5]
Figure 15.2.6. This anatomical illustration presents a sagittal (side-view) cross-section of the human head, neck, and upper torso, focusing on the pathway of the esophagus and its relationship to surrounding structures. At the top of the diagram, the oral and nasal cavities are visible, along with the pharynx region where the respiratory and digestive tracts intersect. The trachea (windpipe) is labeled and shown running anteriorly (toward the front) as it descends into the chest cavity. Positioned posteriorly (behind) the trachea, the esophagus is depicted as a long, tubular structure that extends from the pharynx downward through the neck and chest to reach the stomach. Two critical sphincters are labeled along the esophagus: the upper esophageal sphincter, located at the junction between the pharynx and the beginning of the esophagus in the neck region, and the lower esophageal sphincter, positioned at the distal end where the esophagus meets the stomach. These sphincters are muscular rings that control the movement of food and prevent backflow. The stomach is partially visible at the bottom of the diagram. This illustration effectively demonstrates the anatomical course of the esophagus and the key regulatory structures that facilitate swallowing and digestion while preventing reflux. [Return to Figure 15.2.6]
Figure 15.2.7. This three-panel anatomical diagram illustrates the sequential phases of swallowing (deglutition) through sagittal cross-sections of the head, neck, and upper torso. Each panel shows the same anatomical structures with different muscle groups highlighted in red to demonstrate their active roles during each phase. The left panel depicts the buccal phase (voluntary), showing the tongue forming a bolus of food in the oral cavity, with the superior pharyngeal constrictor muscle and medial pharyngeal constrictor muscle labeled. During this voluntary phase, the tongue pushes the bolus toward the back of the mouth to initiate swallowing. The middle panel shows pharyngeal-esophageal phase part 1 (involuntary), where the medial and inferior pharyngeal constrictor muscles are highlighted and labeled, demonstrating how these muscles contract sequentially to propel the bolus through the pharynx. The right panel illustrates pharyngeal-esophageal phase part 2 (involuntary), highlighting the inferior pharyngeal and esophageal constrictor muscles as they continue the involuntary peristaltic wave that moves the bolus down the esophagus toward the stomach. Throughout all three phases, the anatomical structures including the nasal cavity, oral cavity, pharynx, larynx, trachea, and esophagus remain visible, providing context for understanding how the coordinated muscular contractions facilitate the complex process of swallowing. [Return to Figure 15.2.7]
Report an Error
Did you find an error, typo, broken link, or other problem in the text? Please follow this link to the error reporting form to submit an error report to the authors.
